Wednesday, October 22, 2014

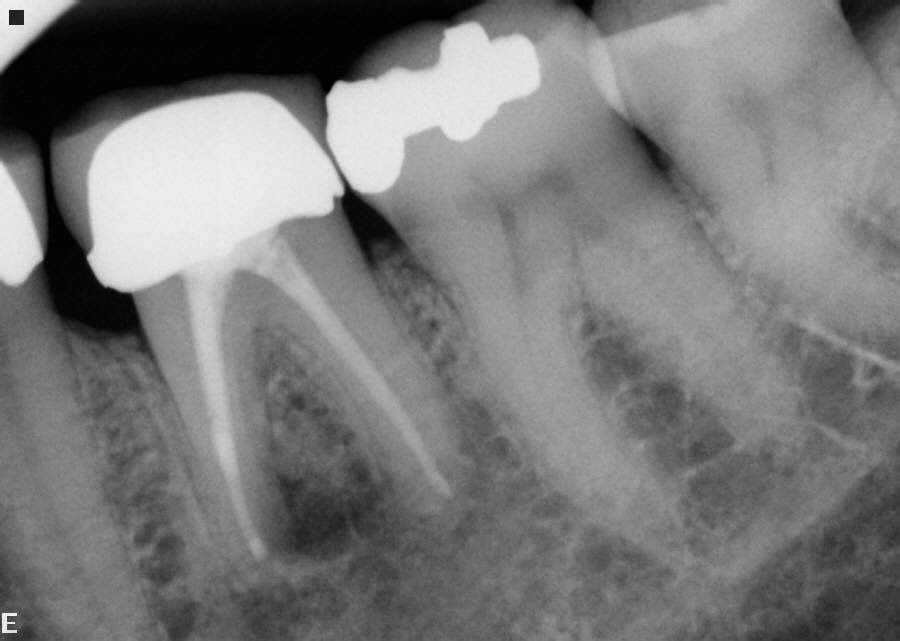
Case 37 Five canals more common than we think

Pre-operative x-ray #19

Patient presented with swelling and painful to bite.


Photo showing pulp chamber floor #19


Once the pulp chamber was clear, five canals clearly visible. Note: The fifth canal is usually in the isthmus area between distal buccal and distal lingual systems, if in the distal root. 


Post-operative x-ray #19


All canals were filled to the apex.


Comments: Usually if there are five canals you will find three in the mesial root more often than the distal root. Three canals in the either root are usually not three separate canals.  In my experience, a third canal either joins the  buccal or lingual canal system.  I can tell you from surgically treating first molars, that the isthmus area many times is the cause of periapical problems because the isthmus has not been or cannot be cleaned adequately.

Tuesday, October 14, 2014

Case 36 Lateral canals can be important.

Preoperative x-ray #4


Tooth is symptomatic.


Immediate post operative x-ray #4


Obturation with 2 lateral canals.


2 month post operative check #4


Tooth is asymptomatic.


6 year post operative x-ray #4


Note: resorption of lateral canal filling material.  Probably just sealer only, gutta percha does not dissolve. Lateral lesions have healed.
Please note: Apical lesion on #5.


7 year post operative xray


All lesions have healed around #4 and no evidence of lateral canals being filled.  Root canal was completed on #5.


Comments:
If lateral canals are not filled i.e. cleaned, there is a good chance that a tooth's apical area will never heal. 

In most cases, it is impossible to mechanically cleanse an lateral canal system. However, sodium hyperchloride may chemically clean a lateral canal. In most of my cases, if a lateral canal is filled it is with softened gutta percha and sealer.  This is speculation on my part, however. 

Wednesday, October 1, 2014

Case 35 Apicoectomy vs. Orthograde Retreatment


Pre-operative x-ray #19

Root canal completed by another provider with separated file in ML canal.  Tooth is extremely symptomatic.


Post-operative x-ray #19


Surgical approach was decided upon and no fractures noted. Three retro fills were placed, and a separated file was removed from ML canal with ultrasonics.  Despite large size of lesion and the amount of bone loss, the prognosis was good. 


3 month check-up #19

Patient is asymptomatic and healing was noted.


9 month check-up #19

Patient continues to be asymptomatic and the bone almost completely filled in


Comments:  Separated instruments are just a way of life for those who do root canal therapy.  The instrument itself is not a problem.  What it represents is: a blockage of a possible dirty canal.  In this case, I just speculated that the separated instrument was the cause of this patient's problem.  Do I know this for sure? No.  Therefore all canals were retrofilled.

Wednesday, July 9, 2014

Case 34 Another look required prior to crown?

Pre-operative x-ray #19


Distal canal not negotiated and a mesial lingual canal not negotiated.  Tooth is symptomatic and very tender to percussion.


Immediate post-operative x-ray #19

I was able to negotiate the distal canal and mesial lingual canal to the radiographic apex.  I was not able to fully negotiate the mesial buccal canal.


6 month post-operative check appointment


The tooth is asymptomatic. Almost complete resolution of the apical lesion of the mesial root is noted.


Comments:
Before final cementation of a crown on a tooth that has a "partial" root canal, my best recommendation is that a second opinion is necessary on a questionable root canal.  Too many patients are upset when I have to penetrate a new crown to "complete" a root canal that is only partially done and they were not aware.  I must admit, I don't know what a patient has been told, only what they tell me.  If questions occur and the patient is irritated, I will always call whomever placed the final crown to see if they have told the patient about the possibility of any future problems, i.e. is there something written in the patient's chart notes? As always, communication between providers is key.

Wednesday, July 2, 2014

Case 33 MTA obturation

Pre-operative x-ray #8
Immediate Post-operative x-ray #8


Symptomatic # 8 which has been apically resorped.


Obturation with MTA entirely.


4 month check x-ray #8

3 year check x-ray #8
After 4 months, asymptomatic with marked apical healing.


After 3 years, asymptomatic with apical radiolucency entirely resolved.


Comments:
In my clinical experience with the use of MTA, which I admit is extremely hard to handle, obturation of canals where the root structure has had resorption, results seem to be very positive. I fill the entire canal system with MTA, never using gutta percha. 

Wednesday, June 25, 2014

Case 32 - More examples of long canal systems

Patient 1 Post-operative x-ray #19
Patient 1 pre-operative x-ray #19

Patient 2 post-operative x-ray #18


Patient 2 pre-operative x-ray #18


Patient 3 post-operative x-ray #31

Patient 3 pre-operative x-ray #31


Patient 4 post-operative x-ray #3


Patient 4 pre-operative x-ray 3


Comments:
Long canals measured over 25 mm pose not only obturation problems, but cleaning problems as well. Recapitulation is mandatory.  I use not only hand instrumentation, but use rotary instruments back and forth to ensure I clean to the apical stop.  Filling vertically can be very difficult and the master cone should fit within 1-2 mm of the apical stop. Vertical condensation will drive the cone to the end of the canal.

Thursday, June 19, 2014

Case 31 Long Canal Systems (25+ mm)

Pre-operative x-ray # 11


Patient was very symptomatic and swollen, it was necessary to place a drain to get her out of pain.  In my practice, drain placement involves incising gum tissue and also exposing the root tip of the tooth to ensure drainage.


Post-operative x-ray #11


Tooth #11 with a working length of 31 mm and numerous lateral apical canals.


Comments:
In my practice I consider a long canal to be over 25 mm in length. Teeth with long canals are the palatal roots of upper molars and maxillary cuspids. Gutta percha comes usually 30 mm in length.  I see many canal systems in which the apical 3-4 mm is never filled in long canals, which probably means this area was not cleaned successfully either, therefore, having a greater risk of failure. If you are going to treat these types of canals, longer files, i.e. 30 mm files are necessary.